
Integrated Intake Referral Form

Your submission of this form will be taken to explicitly mean that the patient has given their permission to make the referral and to disclose appropriate personal health information for initiating the services of our Bethell Hospice (BH) palliative care physicians.

Referral Eligibility

  • Patient has prognosis of less than 6 months with PPS ≤ 60%.
  • Patient is connected to home care services through Ontario Health at Home – Central West. If not, please initiate.
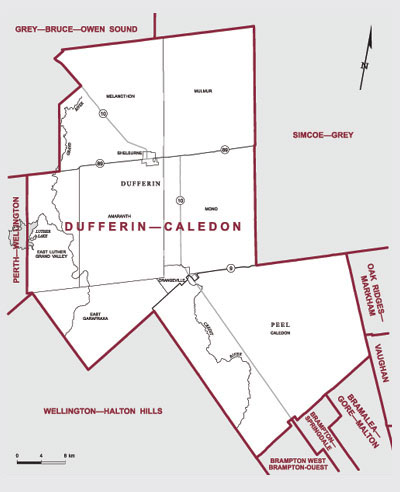
  • Patient lives in catchment area of Dufferin-Caledon (view map).
  • Referral is NOT solely for MAiD provision.
  • Referral source (or Family Physician) remains MRP until patient is seen and accepted by BH Community Physicians.
  • Referral source (or Family Physician) agrees to resume MRP status if patient improves and no longer meets referral criteria.
  • All physicians agree to stop billing G512 code once patient accepted to BH Community Physician team.
Patient Information

Choose all that apply. Hold Ctrl (Windows) or Command (Mac) to select more than one.

Palliative Care Needs

Choose all that apply. Hold Ctrl (Windows) or Command (Mac) to select more than one.

Medical History and Precautions

Choose all that apply. Hold Ctrl (Windows) or Command (Mac) to select more than one.

Family Doctor

Ontario Health at Home Care Coordinator

Community Nursing

Other Provider

Emergency Contact

Referral Details

Individual Completing the Form

Referring Physician

Supporting Documents

If you have supporting documents, such as a medication list, please fax them to 905-838-0302.

Important: Please ensure you have provided your cell phone or backline phone number so our intake team and MD can speak to you directly.

For further information about our referral process, eligibility criteria or general inquiries, please contact 905.838.3534 ext. 2252.

Additional Information